Albumin-creatinine ratio
350 UAH
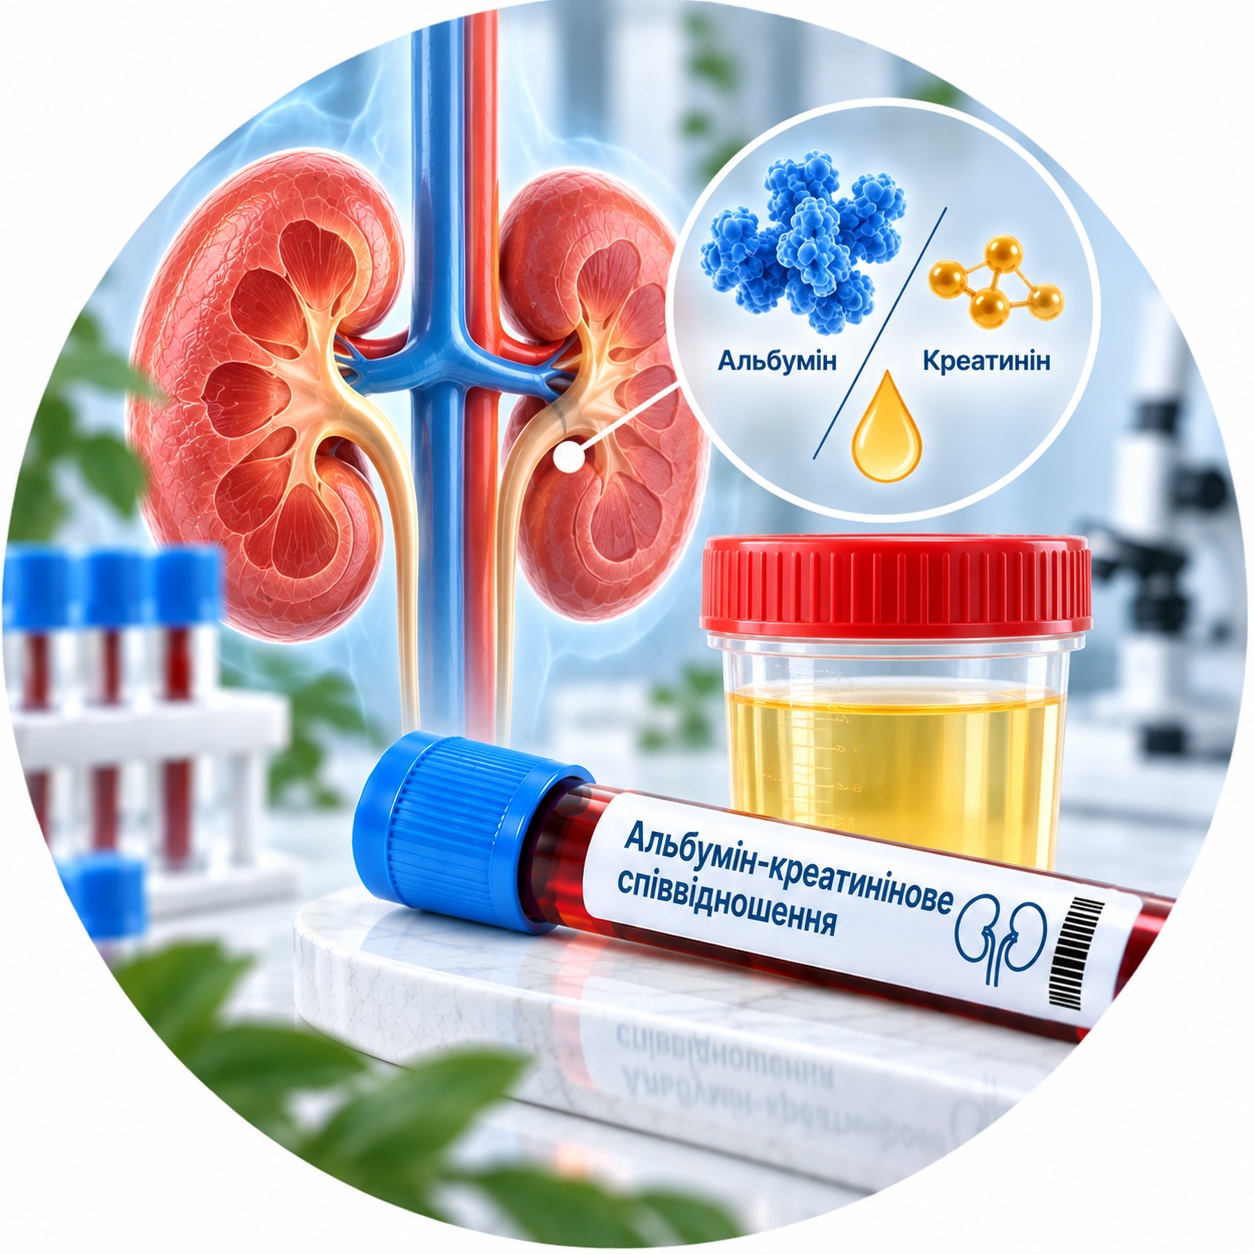
Laboratory research albumin-creatinine ratio (ACR) in urine is the "gold standard" for early diagnosis of diabetic nephropathy, damage to renal filters, and assessment of cardiovascular risks.
Deadline: 1 business day
Biomaterial: Morning urine sample (single)
Research method: Immunoturbidimetric / Kinetic
Appointment: Microalbuminuria screening, kidney function monitoring in type 1 and type 2 diabetes, arterial hypertension, systemic diseases and chronic kidney disease (CKD).
Urine Albumin-to-Creatinine Ratio (UACR) is a highly sensitive laboratory indicator that is calculated as the ratio of the concentration of albumin in the urine to the level of creatinine in the same sample.
Normally, healthy kidney glomeruli almost do not pass albumin (the main protein of blood plasma) into the urine. The appearance of even a minimal amount of albumin (microalbuminuria) is the earliest sign of damage to the renal vascular bed.
Since the concentration of substances in a single urine sample depends on the level of hydration (the amount of fluid consumed), isolated measurement of albumin can be misleading. Creatinine is excreted by the kidneys at a relatively constant rate, so calculating the ratio albumin/creatinine completely eliminates the effect of urine dilution or concentration. This makes a single morning urine sample as informative as a difficult-to-collect 24-hour (24-hour) analysis.
Indications for appointment
Type 1 and 2 diabetes: Annual screening for early detection of diabetic nephropathy (starting 5 years after diagnosis for type 1 and immediately upon diagnosis for type 2).
Arterial hypertension: Assessment of target organ damage (renal vessels) and calculation of cardiovascular risks.
Chronic kidney disease (CKD): Diagnosis, staging and monitoring of the effectiveness of nephroprotective therapy.
Cardiovascular diseases: Assessing the risk of developing coronary heart disease, heart failure, and stroke.
Systemic and autoimmune diseases: Systemic lupus erythematosus, vasculitis, amyloidosis.
Pregnancy: Screening for the risk of developing preeclampsia in high-risk women.
Interpretation of results
The reference values given are approximate. The final interpretation and diagnosis is made by the doctor, taking into account the clinical history.
Reasons for increased ACS (over 30 mg/g):
Early stages of diabetic or hypertensive nephropathy.
Glomerulonephritis, pyelonephritis, polycystic kidney disease.
Heart failure, severe atherosclerotic disease.
Temporary (physiological) increase: fever, acute infectious diseases, intense physical exertion, dehydration, high-protein diet, decompensated diabetes mellitus (high glycemia).
Preparation for the study
Material: An average portion of the first morning urine is used for analysis.
Hygiene procedures: Before collecting urine, it is imperative to thoroughly clean the external genitalia without using aggressive detergents.
Container: The collection is carried out in a special sterile plastic container for urine.
Restrictions on the eve: 24 hours before the test, you should avoid intense exercise, alcohol, spicy, fatty foods, and foods that change the color of your urine (beets, carrots).
Exclusion factors: Do not take the test during menstruation, with acute inflammatory diseases of the urinary system (cystitis, urethritis), as well as with high body temperature (you need to wait 2–3 days after recovery).
Frequently Asked Questions (FAQ)
1. Why is it better to take the ASK in a single urine sample than to collect daily urine? Daily urine collection is often accompanied by errors (missed portion, violation of storage conditions). Calculation of the albumin/creatinine ratio in first morning urine compensates for concentration fluctuations and provides the same accuracy without everyday discomfort.
2. Does a single increase in ASK mean that my kidneys are failing? No. The ACS index is very sensitive and can temporarily increase due to stress, exercise, colds, or high blood pressure. To confirm a diagnosis (for example, diabetic nephropathy), the doctor usually orders a repeat test 2–3 times over 3–6 months.
3. What tests should this study be combined with? For a comprehensive assessment of the kidneys, AKS is most often prescribed together with a calculation glomerular filtration rate (GFR), analysis on creatinine and urea in the blood, as well as a complete urinalysis and glycated hemoglobin (HbA1c) in diabetes.
Recommendations after receiving the results
Contact a specialist. The results of the analysis should be evaluated by an endocrinologist, nephrologist, or therapist (family doctor).
With indicator A2 (30–300 mg/g): The doctor may adjust antihypertensive or hypoglycemic therapy (in particular, prescribe drugs with nephroprotective effects - ACE inhibitors or ARBs).
Control of risk factors: Regularly monitor blood pressure (target values < 130/80 mm Hg) and blood glucose levels, and follow a low-salt diet.
| Execution time | 1 day |
|---|---|
| Type of biomaterial | daily diuresis |
Useful tests